Fascitis plantar
Revisado por Dr Philippa Vincent, MRCGPÚltima actualización por Dr Toni Hazell, FRCGPÚltima actualización 1 Oct 2026
Cumple con las directrices editoriales
- DescargarDescargar
- Compartir
- Language
- Discusión
- Ask Patient
- Versión en audio
- Agregar a fuentes preferidas en Google
Profesionales Médicos
Los artículos de Referencia Profesional están diseñados para ser utilizados por profesionales de la salud. Están escritos por médicos del Reino Unido y se basan en evidencia de investigación, así como en guías del Reino Unido y Europa. Puede encontrar el Fascitis plantar artículo más útil, o uno de nuestros otros artículos de salud.
¿Qué es la fascitis plantar?
Plantar fasciitis continues to be widely used for the clinical syndrome of undersurface heel pain. However, the use of 'itis' denotes an inflammatory disorder. This is a misnomer as plantar fasciitis is a degenerative rather than an inflammatory condition.1
The plantar fascia is a thick, fibrous band of connective tissue. Its origin is the medial plantar tubercle of the calcaneum. It runs along the sole of the foot like a fan, being attached at its other end to the base of each of the toes. It is a tough, resilient structure that has a number of critical functions during running and walking:
It stabilises the metatarsal joints during impact with the ground.
It acts as a shock absorber for the entire leg.
It forms the longitudinal arch of the foot and helps to lift the arch to prepare it for the 'take-off' phase of the gait cycle.
Plantar fasciitis pathophysiology21
Plantar fascia and Achilles tendon
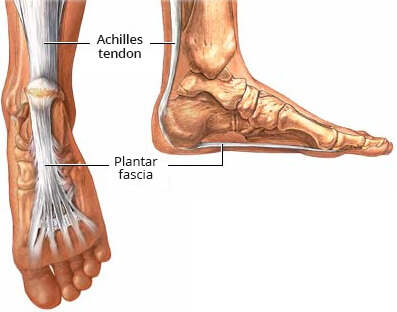
The plantar fascia is a sturdy structure but the degree of stress that it takes makes it susceptible to injury. A force equal to almost three times the body's weight passes through the foot with each step. On running, this typically happens about 90 times a minute.
Plantar fasciitis is thought to be a traction and overuse injury. Damage to the plantar fascia is usually in the form of micro-tears. Plantar fasciitis is a degenerative rather than an inflammatory process.
Damage tends to occur near the heel, where stress on the fibres is greatest and where the fascia is the thinnest. The fascia broadens as it extends toward the toes.
Plantar fasciitis is often associated with calcaneal (heel) spurs. These are depositions of calcium where the fascia suffers most damage. Spurs are most commonly on the medial side at the origin of the fascia from the calcaneum. Spurs are the result of the process of plantar fasciitis and not the cause of the pain.
Plantar fasciitis can present bilaterally.1
Epidemiología
Plantar fasciitis is common in runners but can also affect sedentary people.3
Plantar fasciitis risk factors4
Intrinsic:
Pes planus.
Pes cavus.
Over-pronation or limited dorsiflexion of the ankle.
Leg-length discrepancy.
Excessive lateral tibial torsion.
Excessive femoral anteversion.
Tener sobrepeso.
Gastrocnemius and soleus muscles tightness.
Achilles tendon tightness.
Gastrocnemius, soleus and intrinsic foot muscles weakness.
Ageing of the heel fat pad.
Atrophy of the heel fat pad.
Plantar fascia stiffness.
Extrinsic:
Overuse eg, prolonged standing or jumping.
Mechanical stresses and micro-tearing.
Incorrect training: a too-fast increase in the distance, intensity, duration, or frequency of activities that involve repetitive impact loading of the feet.
Inadequate or inappropriate footwear.
Historia
The principal complaint is heel/plantar pain. Most often this is 1 or 2 cm distal to the medial calcaneal tuberosity.
Ask about the onset of the symptoms and any precipitating, aggravating, or relieving factors. What brings it on? What makes it worse?
Plantar fasciitis is often at its most severe during the first few steps after prolonged inactivity, such as sleeping or sitting.
Sitting with the foot elevated usually relieves the pain.
For those who are on their feet all day, pain is worst at the end of the day.
Walking barefoot, on toes, or up stairs can precipitate pain.
Ask about running or jogging and other sports.
Ask about footwear and when it was last replaced.
Ask about previous trauma to the foot.
Examen
Look at the foot. Note any obvious deformities, skin changes, or congenital conditions. Look for pes planus or pes cavus.
There is often tightness of the Achilles tendon and ankle dorsiflexion may be limited.
Palpate the plantar surface over the medial calcaneal tuberosity and along the course of the plantar fascia, pressing quite hard. The reproduction of the pain is the most important physical sign to confirm the diagnosis.
Pain may be reproduced by asking the patient to stand on their toes or by passive dorsiflexion of the toes.
Palpate the back of the heel and ankle to exclude Achilles tendonitis.
Subcalcaneal bursitis produces a tender swelling underneath the calcaneum. It is not aggravated by dorsiflexing the toes. There is usually little or no swelling in plantar fasciitis.
Referred pain from an S1/S2 lesion should be excluded. Perform the straight leg raising test as for examination of the back. Check the ankle tendon reflex (S1) and calf strength. This is easily performed by asking the patient to walk on toes or stand on one leg and raise the heel off the floor. These tests should be normal.
Exclude tarsal tunnel syndrome: the posterior tibial nerve passes under the flexor retinaculum which runs between the medial malleolus and the calcaneum. Percuss over the nerve below and posterior to the medial malleolus. This can reproduce pain, numbness and burning on the medial side of the foot, ankle, or calf if there is tarsal tunnel syndrome.
Press together the heads of the 2nd and 3rd metatarsals and then the 3rd and 4th. Reproduction of the pain suggests Morton's neuroma, with entrapment of the common digital nerve between the metatarsal heads.
A stress fracture of the calcaneum will cause tenderness over the calcaneum rather than anterior to it.
Diagnóstico diferencial
Vea también el separado Pie dolorido y Fracturas y dislocaciones del pie artículos.
Bursitis subcalcánea.
S1 radiculopathy or referred pain.
Neuroma de Morton.
Enfermedad de Sever (children and adolescents).
Stress fracture of calcaneum.
Very rarely:
Fibrosarcoma.
Metastases.
Cuerpo extraño.
Gota.
Investigaciones15
The diagnosis is essentially clinical. However, imaging may be required to exclude other possible underlying conditions.
Blood tests are not helpful.
X-ray: should not be performed as a matter of routine but may be indicated if you suspect another diagnosis. A lateral view may show soft tissue calcifications or a calcified spur on the anterior aspect of the calcaneus. X-ray may also help to exclude stress fracture, although stress fractures may not always be evident.
Ultrasound: this may show a thicker heel aponeurosis or plantar fascia in plantar fasciitis.
MRI is occasionally used in patients who are not responding to standard management; it may detect a stress fracture, tear of the plantar fascia or osteochondral defect in the cartilage and bone of the foot or ankle.
Plantar fasciitis treatment and management
Treatments include stretching and physiotherapy, orthotics, extracorporeal shock wave therapy (ESWT) and corticosteroid injections (CSI), given either with lidocaine or protein rich plasma (PRP). General advice would include rest when pain is severe and weight loss in the case of overweight or obesity. Non-steroidal anti-inflammatory drugs and ice may be useful. Runners should run on a soft surface where possible and wear laced shoes which are replaced regularly, as well as considering the use of orthotics. During severe symptoms, a temporary shift to swimming, cycling, a step machine in a gym, or other low-impact exercise may be helpful.
Physiotherapy and stretching exercises
Treatment with physio (which may include deep massage of the plantar fascia) and exercises alone will take at least 6-8 weeks to see an improvement and recent systematic reviews suggest that the trend towards improvement with physiotherapy alone is non-significant, with most benefit being in the short-term. The addition of kinesiology taping or ESWT (discussed later) improve prognosis. 26
Orthotics, splinting and casting
There is some evidence that full-length orthotics relieve symptoms to a greater extent than those which just cover the heels.
Combining these with night splints (which keep the ankle dorsiflexed and the toes extended) or rocker shoes can show a greater improvement compared with either of the three interventions alone. 7
Corticosteroid injection (CSI)
CSI can be given in combination with lidocaine or PRP and there is some evidence that a CSI with PRP is more beneficial than one given with lidocaine, particularly when it comes to long-term improvement in pain and function. 8981
Ultrasound guidance is often used to facilitate accurate injection. 10
Such injections are not part of routine primary care and would be done by a GP with an extended role in musculoskeletal medicine, as part of a separately commissioned service, or in secondary care.
Adverse effects include fat pad necrosis, skin atrophy, rupture of the plantar fascia and (very rarely) infection such as osteomyelitis. 11CSI are usually limited to 2-3 injections per year, to reduce the risk of adverse effect.
Extracorporeal shock-wave therapy (ESWT)
There is evidence for ESWT causing a reduction in pain intensity as well as improvement in functional outcomes, with some studies showing that it is more beneficial than CSI. It is generally a safe treatment. 1213
The most recent National Institute for Health and Care Excellence (NICE) guidance (which has not been updated since 2009) says that evidence is inconsistent and that it should only be used with special arrangements for clinical governance, consent and audit, or research.14 It is however offered by the NHS and private sector in many areas.
Botulinum toxin A injections
This may produce some benefit in the short term and would generally be used when first-line therapies have not helped. 15
More evidence is probably needed before this becomes more widely used. 16
Radioterapia
Cirugía
Endoscopic fasciotomy may be required in patients who continue to have pain that limits activity and function despite exhausting non-operative treatment options.3
Further research is needed to fully establish long-term outcomes. 19
Plantar fasciitis prognosis
Pain may be long-standing and can last for some years, but 75% show spontaneous response within 12 months.1
It is important to avoid the vicious cycle whereby walking is painful and therefore the patient becomes progressively more inactive and potentially gains weight, thus worsening the pain. 20
Plantar fasciitis prevention
Regularly changing footwear used for running and walking.
Usar zapatos con buen acolchado en los talones y buen soporte para el arco.
Perder peso si tiene sobrepeso.
Avoiding exercising on a hard surface.
Regular stretching exercises for the plantar fascia and Achilles tendon.
Actualizaciones exclusivas para profesionales de la salud
Mantente informado con las últimas actualizaciones clínicas, perspectivas profesionales y orientación basada en evidencia. El boletín de Patient Pro selecciona contenido esencial para profesionales de la salud, entregado directamente en tu bandeja de entrada.
Al suscribirte aceptas nuestros Política de Privacidad. Puedes darte de baja en cualquier momento. Nunca vendemos tus datos.
Lecturas adicionales y referencias
- Buchanan BK, Kushner D; Plantar Fasciitis. StatPearls, July 2021.
- Buchanan BK, Kushner D; Plantar Fasciitis. StatPearls, July 2021.
- Schwartz EN, Su J; Plantar fasciitis: a concise review. Perm J. 2014 Winter;18(1):e105-7. doi: 10.7812/TPP/13-113.
- Trojian T, Tucker AK; Plantar Fasciitis. Am Fam Physician. 2019 Jun 15;99(12):744-750.
- Petraglia F, Ramazzina I, Costantino C; Plantar fasciitis in athletes: diagnostic and treatment strategies. A systematic review. Muscles Ligaments Tendons J. 2017 May 10;7(1):107-118. doi: 10.11138/mltj/2017.7.1.107. eCollection 2017 Jan-Mar.
- Aggarwal P, Jirankali V, Garg SK; Evaluation of plantar fascia using high-resolution ultrasonography in clinically diagnosed cases of plantar fasciitis. Pol J Radiol. 2020 Jul 24;85:e375-e380. doi: 10.5114/pjr.2020.97955. eCollection 2020.
- Raj S, Sharma C, Sundus H; Effect of Different Physiotherapeutic Interventions in Plantar Fasciitis: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. Musculoskeletal Care. 2025 Sep;23(3):e70151. doi: 10.1002/msc.70151.
- Schuitema D, Greve C, Postema K, et al; Effectiveness of Mechanical Treatment for Plantar Fasciitis: A Systematic Review. J Sport Rehabil. 2019 Oct 18;29(5):657-674. doi: 10.1123/jsr.2019-0036. Print 2020 Jul 1.
- Seth I, Bulloch G, Seth N, et al; The role of corticosteroid injections in treating plantar fasciitis: A systematic review and meta-analysis. Foot (Edinb). 2023 Mar;54:101970. doi: 10.1016/j.foot.2023.101970. Epub 2023 Feb 3.
- Sharma R, Chaudhary NK, Karki M, et al; Effect of platelet-rich plasma versus steroid injection in plantar fasciitis: a randomized clinical trial. BMC Musculoskelet Disord. 2023 Mar 7;24(1):172. doi: 10.1186/s12891-023-06277-1.
- Doan HN, Choo YJ, Chang MC; Comparison of Effectiveness Between Ultrasound-Guided and Blind Corticosteroid Injections in Plantar Fasciitis: A Systematic Review and Meta-Analysis. Life (Basel). 2025 Jul 15;15(7):1107. doi: 10.3390/life15071107.
- Mohd Khalid SA, Bajuri MY; Unexpected sequelae of plantar fasciitis: Iatrogenic calcaneal osteomyelitis following plantar heel injection. Malays Fam Physician. 2019 Dec 31;14(3):80-83. eCollection 2019.
- Melese H, Alamer A, Getie K, et al; Extracorporeal shock wave therapy on pain and foot functions in subjects with chronic plantar fasciitis: systematic review of randomized controlled trials. Disabil Rehabil. 2022 Sep;44(18):5007-5014. doi: 10.1080/09638288.2021.1928775. Epub 2021 May 26.
- Lippi L, Folli A, Moalli S, et al; Efficacy and tolerability of extracorporeal shock wave therapy in patients with plantar fasciopathy: a systematic review with meta-analysis and meta-regression. Eur J Phys Rehabil Med. 2024 Oct;60(5):832-846. doi: 10.23736/S1973-9087.24.08136-X. Epub 2024 Sep 11.
- Terapia de ondas de choque extracorpóreas para fascitis plantar refractaria; NICE HealthTech Guidance (August 2009)
- Iziki C, Skalli S, Lahbabi L, et al; Botulinum Toxin Type A in the Management of Plantar Fasciitis: A Step Forward in Pain Relief. Cureus. 2025 Aug 18;17(8):e90415. doi: 10.7759/cureus.90415. eCollection 2025 Aug.
- Li Q, Zhang J, Sun J, et al; Therapeutic efficacy and safety of botulinum toxin A injection in plantar fasciitis: A systematic review and meta-analysis. PLoS One. 2024 Dec 17;19(12):e0312908. doi: 10.1371/journal.pone.0312908. eCollection 2024.
- Niewald M, Seegenschmiedt MH, Micke O, et al; Randomized, multicenter trial on the effect of radiation therapy on plantar fasciitis (painful heel spur) comparing a standard dose with a very low dose: mature results after 12 months' follow-up. Int J Radiat Oncol Biol Phys. 2012 Nov 15;84(4):e455-62. doi: 10.1016/j.ijrobp.2012.06.022. Epub 2012 Jul 25.
- Badakhshi H, Buadch V; Low dose radiotherapy for plantar fasciitis. Treatment outcome of 171 patients. Foot (Edinb). 2014 Dec;24(4):172-5. doi: 10.1016/j.foot.2014.07.005. Epub 2014 Aug 1.
- Nayar SK, Alcock H, Vemulapalli K; Surgical treatment options for plantar fasciitis and their effectiveness: a systematic review and network meta-analysis. Arch Orthop Trauma Surg. 2023 Aug;143(8):4641-4651. doi: 10.1007/s00402-022-04739-0. Epub 2023 Jan 3.
- Orchard J; Plantar fasciitis. BMJ. 2012 Oct 10;345:e6603. doi: 10.1136/bmj.e6603.
Sobre el autorVer biografía completa
Actualizado por

Dr Toni Hazell, FRCGP
MBBS, BSc, FRCGP, DFSRH, Dip GU med, DRCOG, DCH (London, UK, 2000)
La Dra. Toni Hazell se graduó de la Escuela de Medicina del Hospital St. Mary y realizó su VTS en el Hospital Northwick Park.
Acerca del revisorVer biografía completa

Dra. Philippa Vincent, MRCGP
Médico General, Autor Médico
MB BS, Bsc, MRCGP (2000), DCH, DFSRH, DRCOG
Dra Philippa Vincent es un médico de cabecera del NHS que trabaja en el norte de Londres.
Acceso sencillo a tratamientos y servicios de salud confiables en línea.
Common conditions
Get help with common conditions through the NHS, without a GP appointment.
 Sinusitis aguda
 Amigdalitis bacteriana
 Impetigo
 Picaduras de insectos
 Herpes zósterInfección del tracto urinario (ITU)
Más en ortopedia y medicina deportiva
- Marcha anormal
- Articulaciones dolorosas: evaluación, investigaciones y manejo en atención primaria
- Monoartritis aguda
- Fractura de Bennett y otras lesiones del pulgar
- Enfermedad de Blount
- Tumores óseos
- Enfermedad de Bornholm
- Fractura de clavícula
- Síndrome de aplastamiento
- Síndrome del túnel cubital
- Displasia del desarrollo de la cadera
- Lesiones en la mano y su evaluación
- Enfermedad ósea de Köhler
- Desgarros meniscales y otras lesiones del cartílago de la rodilla
- Fracturas pélvicas
- Bursitis prepatelar
- Enfermedad de Scheuermann
- Enfermedad de Sinding-Larsen Johansson
- Fracturas por estrés
- Fracturas del arco cigomático y orbital