Leucemia linfoblástica aguda
ALL
Revisado por Dr John Cox, MRCGPÚltima actualización por Dr Laurence KnottÚltima actualización 19 de mayo de 2016
Cumple con las directrices editoriales
- DescargarDescargar
- Compartir
- Language
- Discusión
- Ask Patient
- Versión en audio
- Agregar a fuentes preferidas en Google
Aviso sobre el contenido
Esta página no se ha revisado recientemente, por lo que es posible que haya cambiado parte de la información o que algunos enlaces externos ya no funcionen.
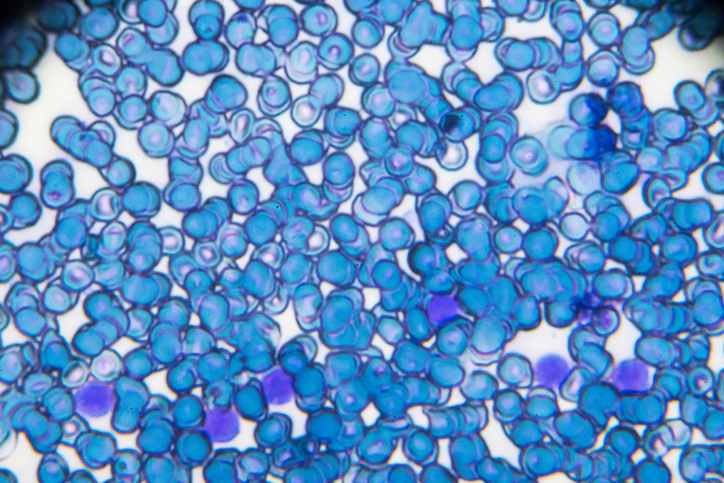
La leucemia linfoblástica aguda (LLA) es una condición en la que la médula ósea produce grandes cantidades de linfocitos inmaduros anormales.
De un vistazo
La leucemia linfoblástica aguda (LLA) es una condición en la que la médula ósea produce grandes cantidades de linfocitos inmaduros anormales.
Es la forma más común de leucemia en niños, aunque puede ocurrir a cualquier edad.
Los síntomas comunes incluyen cansancio, facilidad para tener moretones, infecciones frecuentes, glándulas inflamadas y dolor óseo.
El diagnóstico a menudo implica análisis de sangre y una muestra de médula ósea.
El tratamiento consiste principalmente en quimioterapia, a veces combinada con radioterapia o trasplante de células madre.
La quimioterapia para la LLA implica fases de inducción, consolidación y mantenimiento.
El pronóstico para los niños con LLA es generalmente bueno, y la mayoría logra una cura.
¿Qué es la leucemia linfoblástica aguda?
Acute lymphoblastic leukaemia (ALL) is a condition where the bone marrow makes large numbers of abnormal immature lymphocytes. The immature cells are called lymphoblasts. There are various subtypes of ALL. For example, the abnormal lymphoblasts can be immature B or T lymphocytes. The abnormal lymphoblasts continue to divide and multiply but do not mature into proper lymphocytes. Typically, ALL develops quite quickly (acutely) and rapidly becomes worse (over a few weeks or so) unless treated.
Who develops acute lymphoblastic leukaemia?
ALL can occur at any age, but about 6 in 10 cases occur in children. It is the most common form of leukaemia to affect children (although it is an uncommon disease). It occurs in about 450 children in the UK each year. It can occur at any age in childhood but most commonly develops between the ages of 4 and 7 years. Boys are more commonly affected than girls.
It is less common in adults. It affects around 200 adults in the UK each year. The average age of an adult with ALL is 55 years.
What causes acute lymphoblastic leukaemia?
A leukaemia is thought to start first from one abnormal cell. What seems to happen is that certain vital genes which control how cells divide, multiply and die are damaged or altered. This makes the cell abnormal. If the abnormal cell survives it may multiply out of control and develop into a leukaemia.
In most cases of ALL, the reason why an immature lymphocyte becomes abnormal is not known. There are certain risk factors which increase the chance that leukaemia will develop. However, these only account for a small number of cases. Risk factors known for ALL are high-dose radiation (for example, previous radiotherapy for another condition) and exposure to the chemical benzene.
Some genetic conditions can increase the risk of having ALL in the future. The most common is Síndrome de Down. Genetic means that the condition is passed on through families through special codes inside cells called genes.
ALL is not an inherited condition and does not run in families.
What are the main symptoms and problems when acute lymphoblastic leukaemia develops?
As large numbers of abnormal lymphoblasts are made, much of the bone marrow fills with these abnormal cells. Because of this, it is difficult for normal cells in the bone marrow to survive and make enough normal mature blood cells. Also, the abnormal lymphoblasts spill out into the bloodstream. Therefore, the main problems which can develop include:
Anaemia. This occurs as the number of red blood cells (erythrocytes) goes down. This can cause tiredness, breathlessness and other symptoms. You also look pale.
Problemas de coagulación sanguínea. Esto se debe a niveles bajos de plaquetas. Esto puede causar moretones fáciles, sangrado de las encías y otros problemas relacionados con el sangrado.
Serious infections. The abnormal lymphoblasts do not protect against infection. Also, there is a reduced number of normal white blood cells which usually combat infection. Therefore, serious infections are more likely to develop. Depending on the type and site of infection which develops, the symptoms can vary greatly.
The abnormal lymphoblasts may also build up in lymph glands and the spleen. You may therefore develop swollen glands in various parts of the body, particularly in the neck and armpits, and develop an enlarged spleen. Other common symptoms include an enlarged liver, pain in the bones or joints, persistent high temperature (fever) and weight loss. Without treatment, ALL usually leads to death within a few months.
How is acute lymphoblastic leukaemia diagnosed and assessed?
Un análisis de sangre
A prueba de sangre can often suggest the diagnosis of ALL. The test will typically show a low number of red blood cells (erythrocytes), normal white blood cells (leukocytes) and platelets. The blood test also typically shows a number of abnormal lymphoblasts which are not normally seen in the blood. So, the total white cell count in the blood sample may be high, even though the number of normal white cells is low. Further tests are usually done to confirm the diagnosis.
Una muestra de médula ósea
For this test, a small amount of bone marrow is removed by inserting a needle into the pelvic bone, or sometimes the breastbone (sternum). Local anaesthetic is used to numb the area. Sometimes a small core of marrow will also be taken (a trephine biopsy). The samples are put under the microscope to look for abnormal cells and are also tested in other ways. This can confirm the diagnosis. Consulte el folleto separado titulado Biopsia y Aspiración de Médula Ósea para más detalles.
Análisis de células y cromosomas
Detailed tests are done on abnormal cells obtained from the bone marrow sample or blood test. These find out the exact type of cell that is abnormal - for example, if the abnormal cells are immature B lymphocytes or immature T lymphocytes. The chromosomes within the cells are checked for certain changes.
Chromosomes are the parts in the cell which contain DNA - the genetic makeup of the cell. In some cases of ALL, changes can be detected to parts of one or more chromosome. (These changes in chromosomes only occur in the leukaemia cells, not the normal body cells.) For example, in one abnormality called Philadelphia chromosome, a part of chromosome 9 is found to be moved and attached to part of chromosome 22. Consulte el folleto separado llamado Pruebas Genéticas para más detalles.
Punción lumbar
This test collects a small amount of fluid from around the spinal cord (cerebrospinal fluid, or CSF). It is done by inserting a needle between the bones of the back (vertebrae) in the lower (lumbar) region of the back. By examining the fluid for leukaemia cells, it helps to find out if the leukaemia has spread to the brain and spinal cord. See separate leaflet called Lumbar Puncture for more details.
Varios otros exámenes
A radiografía de tórax, further blood tests and other tests are usually done to assess your general well-being.
What is the treatment for acute lymphoblastic leukaemia?
The aim of treatment is to kill all the abnormal cells. This then allows the bone marrow to function normally again and produce normal blood cells. The main treatment is chemotherapy, sometimes combined with radiotherapy. Stem cell transplant (SCT) is sometimes performed.
The exact treatment regime used in each case (the medicines used, doses, length of treatment, etc) takes into account various factors. This is based on research trials which aim to determine the best treatment for the various subtypes of ALL. Research trials continue to try to find even better treatments. The factors which are taken into account include:
The exact type of ALL (for example, if it is a T-cell or B-cell type).
If the leukaemia cells contain chromosome changes such as the Philadelphia chromosome.
Tu edad, sexo y salud general.
The number of lymphoblasts in the blood when your leukaemia was diagnosed.
Qué tan bien responde la condición a la fase inicial del tratamiento (ver abajo).
Si la leucemia se ha extendido al cerebro y/o la médula espinal.
On the basis of these factors, people with ALL are classed as 'low', 'standard' or 'high' risk. That is, the risk of the leukaemia coming back (relapsing) after 'standard' treatment. More intensive treatment is usually offered if your risk is 'high'.
Quimioterapia
La quimioterapia es un tratamiento que utiliza medicamentos anticancerígenos para matar las células cancerosas o para detener su multiplicación. Consulte el folleto separado llamado Quimioterapia para más detalles.
As many doses of these medicines are likely to be given straight into a vein (intravenously) over a prolonged period, it is usual for a plastic tube to be put into a large blood vessel. This can be a central line in a vein in your chest or a peripheral line in your arm (sometimes called a PICC line). It can be left in place for months until the course of treatment is finished. This means you do not need repeated injections. Medicines can be injected or 'dripped' through the line from time to time when a dose is due.
Chemotherapy for ALL is usually divided into different phases:
Induction remission phase. This is an initial intensive treatment using a combination of medicines. It lasts about 4-6 weeks. This aims to kill most of the leukaemia cells. At the end of this phase there are usually no leukaemia cells (or fewer than 5%) detectable in a blood sample or seen in a bone marrow sample. This is called being 'in remission'. Remission does not mean cure.
Consolidation (Intensification) phase. Further medicines are given in this phase of treatment. This aims to kill any remaining leukaemia cells which may still be present (although not detected by any tests). The treatment can be quite intensive, and given in 'blocks' of treatment several weeks apart. The exact medicines used and the intensity can vary, depending on factors such as whether you are in a high-risk, standard-risk or low-risk category.
Maintenance phase. This phase of treatment is less intensive than the induction and consolidation phases. This phase can last up to two years. The aim of this phase is to kill any remaining leukaemia cells that may have been missed by treatment in the other phases. Maintenance treatment is also given between the blocks of treatment in the consolidation phase.
Treatment of the brain and spinal cord
Abnormal cells sometimes get into the brain and spinal cord. Chemotherapy medicines taken by mouth or injected into the bloodstream do not get into the brain and spinal cord very well. Therefore, chemotherapy medicines are usually injected from time to time over the treatment period directly into the fluid that surrounds the spinal cord and brain. This is done in a similar way to a lumbar puncture (described above) and is called an intrathecal injection. In some cases, radiotherapy to the brain is also used.
Trasplante de células madre (SCT)
SCT - sometimes called bone marrow transplantation - may be performed. It may be used for cases where the leukaemia has come back (recurred) following the usual treatment with chemotherapy. It is also more commonly used for adults with ALL.
Tratamiento de apoyo
Other treatments may include antibiotic or antifungal medicines if infection occurs; blood and platelet transfusions to counter low levels of red blood cells (erythrocytes) and platelets; general supportive measures to overcome side-effects of chemotherapy.
Tratamiento de recaídas
Despite treatment, in up to 1 in 4 cases, the ALL may return (relapse) at some point after treatment. Relapses are treated in a similar way to the initial treatment but the treatment regime is often more intensive.
Nota del editor
A new therapy that involves modifying a person's own immunce cells to fight the cancer has been recommended by NICE and will be available through the Cancer Drugs Fund.
Kymriah, which is given as a single intravenous infusion, is a pioneering CART-cell treatment that has the potential to be a cure for people under the age of 25 with relapsed or refactory B-cell acute lymphoblastic leukaemia (ALL).
A commercial agreement has yet to be reached for use of Kymriah in adult patients.
Efectos secundarios de la quimioterapia
Your doctor will advise on the possible risks and side-effects of your particular treatment regime. Very briefly:
Efectos secundarios durante el tratamiento
The medicines used for chemotherapy are powerful and often cause unwanted side-effects. The medicines work by killing cells which are dividing and so some normal cells are damaged too. Side-effects vary from medicine to medicine.
The most common side-effects are feeling sick (nausea), loss of hair, and an increased risk of infection (as the normal white blood cells (leukocytes) are affected by treatment). Anti-sickness medicines are commonly used to prevent nausea.
Efectos secundarios tardíos
In a small number of cases, problems develop months or years after a period of intensive chemotherapy. For example, some children treated with chemotherapy have problems later in life with puberty and with fertility. There is also a small increased risk of developing a different cancer later in life.
¿Cuál es la perspectiva?
Most children with ALL - about 7-8 in 10 cases - can be cured. The outlook (prognosis) for children has improved greatly over a period of 20 years or so.
Children aged between 1 year and 10 years have the best outlook and are most likely to be cured. The outlook is less good for children aged under 1 year and for children older than 10 years. On average, the outlook for adults is less good than for children but a proportion of adults are cured.
The treatment of cancer and leukaemia is a developing area of medicine. New treatments continue to be developed and the information on outlook above is very general. As mentioned, there are some newer medicines that have been introduced in the last few years and which show promise to improve the outlook. The specialist who knows your case can give more accurate information about the outlook for your particular situation.
The chance of a good response to treatment can vary depending on factors, such as the exact type of ALL.
Selecciones del paciente para Cánceres de sangre

Cáncer
Biopsia y aspiración de médula ósea
Una biopsia de médula ósea es un procedimiento en el que se toma una muestra de tejido del interior de un hueso.
por el Dr. Laurence Knott
Cáncer
Leucemia
La leucemia es un cáncer de las células que producen la sangre. Existen diferentes tipos de leucemia. Si desarrollas leucemia, es importante saber qué tipo es. Esto se debe a que el pronóstico y los tratamientos varían según los diferentes tipos.
por la Dra. Hayley Willacy, FRCGP
Preguntas frecuentes
Si la LLA no es hereditaria, ¿por qué tener síndrome de Down aumenta el riesgo?
Aunque la LLA no se transmite en las familias, algunas condiciones genéticas, como el síndrome de Down, pueden aumentar el riesgo de una persona de desarrollarla. Estas son condiciones donde códigos especiales dentro de las células, llamados genes, se transmiten a través de las familias, pero la LLA en sí misma no es hereditaria.
¿Cuál es la razón de las diferentes fases del tratamiento de quimioterapia para la LLA?
La quimioterapia para la LLA se divide en fases para lograr diferentes objetivos. La fase inicial de 'inducción de remisión' tiene como objetivo matar la mayoría de las células leucémicas. La fase de 'consolidación' luego apunta a cualquier célula restante no detectada por las pruebas. Finalmente, la fase de 'mantenimiento', que dura más tiempo, tiene como objetivo eliminar cualquier célula leucémica restante que podría haber sido pasada por alto por tratamientos anteriores.
¿Por qué es importante tratar el cerebro y la médula espinal por separado para la leucemia linfoblástica aguda (LLA)?
Las células anormales de leucemia a veces pueden llegar al cerebro y la médula espinal. Los medicamentos de quimioterapia regulares, tomados por vía oral o inyectados en una vena, no llegan eficazmente a estas áreas. Por lo tanto, la quimioterapia se inyecta directamente en el líquido que rodea la médula espinal y el cerebro a través de un procedimiento llamado inyección intratecal. En algunos casos, también se utiliza radioterapia en el cerebro.
¿Pueden los adultos esperar el mismo pronóstico positivo del tratamiento para la LLA que los niños?
No, en promedio, el pronóstico para los adultos con LLA es menos favorable que para los niños. Aunque una proporción de adultos se cura, los niños generalmente tienen un mejor pronóstico, especialmente aquellos entre 1 y 10 años.
¿Qué es Kymriah y cómo se relaciona con el tratamiento de la LLA?
Kymriah es un nuevo y pionero tratamiento con células CAR T que implica modificar las propias células inmunitarias de una persona para combatir la leucemia linfoblástica aguda de células B. Se administra como una única infusión intravenosa y tiene el potencial de curar a pacientes menores de 25 años con LLA en recaída o refractaria. Un acuerdo comercial para su uso en pacientes adultos aún está pendiente.
Lecturas adicionales y referencias
- Tratamiento de la Leucemia Linfoblástica Aguda Infantil; Instituto Nacional del Cáncer
- Leucemias mieloblásticas agudas en pacientes adultos: Guías de práctica clínica de la ESMO para diagnóstico, tratamiento y seguimiento; Sociedad Europea de Oncología Médica (Ago 2013)
- Leucemia linfocítica crónica: Guías de práctica clínica de la ESMO para diagnóstico, tratamiento y seguimiento; Sociedad Europea de Oncología Médica (2015)
- Eichhorst B, Robak T, Montserrat E, et al; Leucemia linfocítica crónica: Guías de Práctica Clínica de ESMO para el diagnóstico, tratamiento y seguimiento. Ann Oncol. 2015 Sep;26 Suppl 5:v78-84. doi: 10.1093/annonc/mdv303.
- Leucemia mieloide crónica: Guías de Práctica Clínica de ESMO para el diagnóstico, tratamiento y seguimiento; Sociedad Europea de Oncología Médica (2017)
Sobre el autorVer biografía completa
Actualizado por

Dr Laurence Knott
Médico General, Autor Médico
Licenciatura (Hons) en Bioquímica, MBBS
El Dr. Laurence Knott se graduó en 1973 y tiene una amplia experiencia como Médico General.
Acerca del revisorVer biografía completa

Dr John Cox, MRCGP
MA, MB, B Chir, DCH, DRCOG, MRCP (UK), MRCGP
El Dr. John Cox trabajó como Registrador Médico en el Reino Unido y Nueva Zelanda y como Médico suplente en Nueva Zelanda.
Profesionales Médicos
Looking for more in-depth clinical detail? Our Professional Reference articles are written for doctors, nurses and other healthcare professionals. They include comprehensive clinical guidance, diagnostic information and UK/European evidence summaries. If you need the clinical version, you can read the Professional Reference article on this topic.
Comparte tus pensamientos o experiencias con otros en nuestro comunidades de pacientes.
Acceso sencillo a tratamientos y servicios de salud confiables en línea.
Common conditions
Get help with common conditions through the NHS, without a GP appointment.
 Sinusitis aguda
 Amigdalitis bacteriana
 Impetigo
 Picaduras de insectos
 Herpes zósterInfección del tracto urinario (ITU)
Suscríbete al boletín de Patient
Tu dosis semanal de consejos de salud claros y confiables, escritos para ayudarte a sentirte informado, seguro y en control.
Al suscribirte aceptas nuestros Política de Privacidad. Puedes darte de baja en cualquier momento. Nunca vendemos tus datos.