Miastenia gravis
Revisado por Dra. Rachel Hudson, MRCGPÚltima actualización por Dr Caroline Wiggins, MRCGP Última actualización 21 de mayo de 2025
Cumple con las directrices editoriales
- DescargarDescargar
- Compartir
- Language
- Discusión
- Versión en audio
- Agregar a fuentes preferidas en Google
La miastenia gravis (MG) es una condición en la que los músculos se cansan y debilitan fácilmente. Se debe a un problema con la forma en que los nervios estimulan a los músculos para que se tensen (contraigan). Los músculos alrededor de los ojos son comúnmente los primeros afectados. Esto causa párpados caídos y visión doble. El tratamiento suele ser efectivo. Sin embargo, las recaídas son comunes y muchas personas con miastenia gravis tienen dificultades a largo plazo con sus actividades diarias.
De un vistazo
La miastenia gravis es una rara condición autoinmune en la que el sistema inmunológico ataca por error las conexiones entre los nervios y los músculos.
Causa debilidad muscular que empeora con la actividad y mejora con el descanso.
Los síntomas a menudo afectan los músculos oculares, lo que lleva a párpados caídos o visión doble.
Otros músculos alrededor de la cara, garganta, brazos, piernas y pecho también pueden verse afectados.
El diagnóstico implica verificar la debilidad muscular, realizar análisis de sangre para detectar anticuerpos y escaneos del pecho.
El tratamiento incluye medicamentos para mejorar la fuerza muscular, esteroides y, a veces, cirugía para extirpar la glándula del timo.
Understanding muscle
Each muscle is supplied by a nerve which splits into smaller nerves as they spread along the muscle fibres. There is a tiny gap between the ends of the nerves and the surface of the muscle. This gap is called the neuromuscular junction (see diagram below).
Miastenia gravis
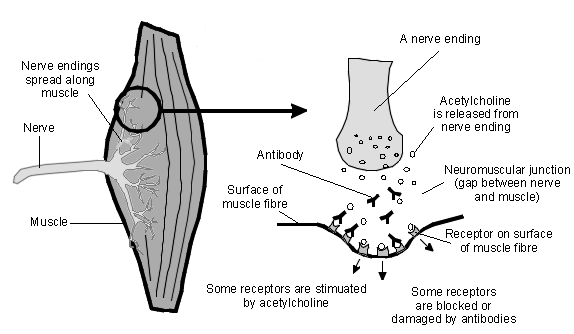
The brain sends messages down the nerves to the muscles it wants to tighten (contract). The nerve endings release a chemical called a neurotransmitter into the neuromuscular junction. This neurotransmitter is called acetylcholine. The acetylcholine moves across the neuromuscular junction and quickly attaches to receptors on the muscles. This triggers the muscle to tighten (contract). There are lots of acetylcholine receptors on each muscle fibre.
What is myasthenia gravis?
People with myasthenia gravis have a fault in the way nerve messages are passed from the nerves to the muscles at the neuromuscular junction. The muscles become easily tired and weak.
What causes myasthenia gravis?
Myasthenia gravis is an autoimmune disease. This means that sistema inmunológico (which normally protects the body from infections) mistakenly attacks itself. (Other autoimmune diseases include diabetes tipo 1 and thyroid disorders.) In most people with myasthenia gravis, antibodies are made which block, alter or destroy the acetylcholine receptors on muscles. The acetylcholine cannot then attach to the receptor on the muscle fibre at the neuromuscular junction and so the muscle is less able to tighten (contract).
What causes the abnormal antibodies to be made?
Myasthenia gravis usually occurs in people whose bodies have particular DNA which makes them more likely to have myasthenia gravis.
The reason why the body's immune system starts to make abnormal antibodies against muscle receptors is not known. Abnormal antibodies are made in various parts of the immune system, including:
The bone marrow.
Blood.
Lymph glands.
The thymus gland.
How common is myasthenia gravis?
Myasthenia gravis is a rare condition. It can occur at any age but most commonly affects women aged between 30 and 40 and men aged 50-70 years. Women are slightly more likely than men to have myasthenia gravis, particularly in certain ethnic backgrounds. It can occur in more than one member of the same family.
What role does the thymus gland have in myasthenia gravis?
The thymus gland is a small gland in the upper chest just behind the breastbone (sternum). It is part of the immune system. The thymus is abnormal in many people with myasthenia gravis. The exact role of the cells in the thymus is not clear. However, the cells may have something to do with programming or making antibodies against acetylcholine receptors. For some people, surgical removal of the thymus gland by an operation can improve their symptoms or allow them to take less medication to manage their symptoms.
A small number of people with myasthenia gravis develop a growth (tumour) of the thymus gland, called a thymoma. If it occurs, it is usually non-cancerous (benign), However, in a very small number of cases it is cancerous (malignant). Removal of the thymoma is recommended in most cases.
What are the symptoms of myasthenia gravis?
The typical main symptom is weakness of muscles that becomes worse with activity and improves with rest. Affected muscles tire or become fatigued very easily. This means that symptoms are usually worse at the end of the day and after exercising. Fatigue is also a very common symptom.
The symptoms vary enormously between people with myasthenia gravis:
The muscles around the eyes are commonly affected first. This causes drooping of the eyelid (ptosis), and double vision (diplopia). In some people, the muscles around the eyes are the only ones affected. This is known as ocular myasthenia and affects 1 in 7 people with myasthenia gravis. Some people with ocular myasthenia (they only have eye symptoms) develop generalised myasthenia (affecting other parts of their body) within the first few years of their symptoms starting.
Muscles around the face and throat are often affected. Difficulty swallowing, slurred speech, voice changes or repeatedly coughing or choking when eating may be the first signs of myasthenia gravis.
Weakness in the arms, legs and neck may develop.
Weakness in the chest muscles sometimes occurs. If this is severe, a myasthenic crisis may result (see below).
The severity of symptoms (how easily the muscles tire) can vary from mild to severe. Most people notice their symptoms are at their most troublesome in the first couple of years. Infection, stress and certain medications can make symptoms worse.
How is myasthenia gravis diagnosed?
It is not uncommon for the diagnosis of myasthenia gravis to take some time. This is because it is a rare condition and the symptoms often start gradually. If a doctor thinks you may have myasthenia gravis they will examine you to check for muscle weakness, and to see if your muscles tire quickly.
Tests that may then be done include the following:
A blood test to detect the abnormal antibodies and confirm the diagnosis in most cases.
Blood tests may be done to look for other autoimmune conditions.
Muscle and nerve tests may be needed in some cases where the diagnosis is not clear. These usually happen in hospital settings.
If you are diagnosed with myasthenia gravis, further tests will include:
More blood tests to look for other autoimmune disease which may exist alongside.
A CT scan of the chest to assess the thymus gland.
Breathing tests are performed in those people who have weakness of the chest muscles.
People who have double vision (diplopia) will have a scan of their brain. This is to check that there are no masses inside the brain which could be causing the double vision. If this scan is normal, the medical team can be more confident the double vision is caused by myasthenia gravis.
What is the treatment for myasthenia gravis?
In most cases, myasthenia gravis can be effectively treated. Often, combinations of these treatments are needed to best control symptoms.
Anticholinesterase medicines
These medicines slow the breakdown of the neurotransmitter acetylcholine when it is released from the nerve endings. More acetylcholine is then available to compete against the abnormal antibodies for the muscle receptors, which then improves the strength of the muscles. These medicines work best when the disease is mild and the level of antibody is low. The most commonly prescribed anticholinesterase medicine is called pyridostigmine. Diarrhoea is a common side-effect of this but it usually resolves without treatment.
Removal of the thymus (thymectomy)
This is an option in some cases and can improve symptoms for some people with myasthenia gravis.
Immunosuppressant medication
Medicamento esteroide
Steroid medication such as prednisolona tablets is often used in the treatment of myasthenia gravis. Steroids suppress the immune system and prevent the abnormal antibodies from being made.
It may take several months for the steroids to have their maximum benefit on your symptoms. Once improved, the dose is usually reduced gradually to find the lowest dose needed to prevent symptoms. This is to try and avoid the long term side-effects of this medicine. In some people, the dose of steroid needed to control the disease may be quite high and lead to side-effects. See the separate leaflet called Oral steroids for more details.
Other immunosuppressant medicines
An immunosuppressant medicine such as azatioprina may be advised in addition to steroid medication. These medicines work by suppressing the immune system. If these medicines are not effective or you are unable to take them, there are alternatives. These alternatives also work to dampen how well your immune system works.
A steroid plus another immunosuppressant tends to be prescribed. This can work better than either alone and allow a lower dose of steroid to be needed, reducing the risk of steroid side-effects.
Myasthenic crisis
A myasthenic crisis occurs when the muscles that control breathing weaken to the point that breathing becomes very difficult. This can happen quickly and may be triggered by an infection, stress or particular medications which can lead to a worsening of symptoms. Admission to hospital for a week or more is usually needed and you are likely to need a ventilator to help you breathe.
Steroids and rapid acting treatments such as plasma exchange (PLEX) or intravenous immunoglobulins (IVIG) may be given to help your body during a myasthenic crisis. The aim of these treatments is to quickly reduce the abnormal antibodies in your body so you can recover.
What is the course of the disease and outlook (prognosis)?
The current available treatment options usually mean that people with myasthenia gravis have a near-normal life expectancy. Treatment usually works well but many people continue to have some symptoms. Myasthenia gravis is a very variable condition and can cause long-term difficulties with daily activities.
Myasthenia crisis is a life-threatening event. When people are diagnosed with myasthenia gravis, they will be given advice about how to reduce the risk of triggering a myasthenia crisis. This involves advice about how to avoid infections, the importance of taking medications as they are prescribed, stopping smoking and the importance of having vacunas to protect against infection.
Selecciones del paciente para Problemas musculares

Huesos, articulaciones y músculos
Calambres en las piernas
Los calambres en las piernas son comunes y más frecuentes en los músculos de la pantorrilla. Pueden ocurrir en cualquier grupo muscular. La causa no se conoce en la mayoría de los casos. Sin embargo, algunos medicamentos y enfermedades pueden causar calambres en las piernas. Los ejercicios regulares de estiramiento de la pantorrilla pueden prevenir los calambres en las piernas. Las tabletas de quinina pueden recomendarse como último recurso si los calambres ocurren con regularidad.
por la Dra. Surangi Mendis, MRCGP
Huesos, articulaciones y músculos
Debilidad muscular
Este folleto examina los tipos de debilidad muscular y discute la amplia gama de problemas que pueden causarlos. Algunas de estas causas son muy comunes y otras son muy raras. Algunas son leves y reversibles; otras no lo son. La mayoría pueden mejorarse con ejercicio y fisioterapia.
por la Dra. Philippa Vincent, MRCGP
Preguntas frecuentes
¿Pueden los cambios en la dieta o el estilo de vida ayudar a manejar la miastenia gravis?
El artículo no menciona específicamente cambios en la dieta o el estilo de vida como un tratamiento o estrategia de manejo para la miastenia gravis. Sin embargo, sí indica que evitar infecciones, manejar el estrés, dejar de fumar y tener inmunizaciones son importantes para reducir el riesgo de desencadenar una crisis miasténica.
¿Qué podría empeorar mis síntomas de miastenia gravis?
Sus síntomas de miastenia gravis pueden empeorar debido a infecciones, estrés y ciertos medicamentos. Es importante estar consciente de estos desencadenantes.
¿Existen terapias alternativas que puedan ayudar con la miastenia gravis?
El artículo se centra en tratamientos médicos establecidos para la miastenia gravis, como medicamentos anticolinesterásicos, timectomía, esteroides y otros inmunosupresores. No contiene información sobre terapias alternativas.
Si tengo miastenia gravis, ¿mis hijos también la tendrán?
El artículo menciona que la miastenia gravis puede ocurrir en más de un miembro de la misma familia y que las personas generalmente tienen un ADN particular que las hace más propensas a desarrollarla. Sin embargo, no especifica el riesgo exacto de transmitirla a los hijos.
¿Con qué frecuencia necesito ver a un médico para el manejo continuo de la miastenia gravis?
El artículo describe el proceso de diagnóstico y las opciones de tratamiento para la miastenia gravis, pero no especifica la frecuencia de las citas de seguimiento ni el monitoreo médico continuo.
Lecturas adicionales y referencias
- Farmakidis C, Pasnoor M, Dimachkie MM, et al; Treatment of Myasthenia Gravis. Neurol Clin. 2018 May;36(2):311-337. doi: 10.1016/j.ncl.2018.01.011.
- Wang S, Breskovska I, Gandhy S, et al; Advances in autoimmune myasthenia gravis management. Expert Rev Neurother. 2018 Jul;18(7):573-588. doi: 10.1080/14737175.2018.1491310. Epub 2018 Jul 4.
- Estephan EP, Baima JPS, Zambon AA; Myasthenia gravis in clinical practice. Arq Neuropsiquiatr. 2022 May;80(5 Suppl 1):257-265. doi: 10.1590/0004-282X-ANP-2022-S105.
- Beloor Suresh A, Asuncion RMD; Myasthenia Gravis
- Narayanaswami P, Sanders DB, Wolfe G, et al; International Consensus Guidance for Management of Myasthenia Gravis: 2020 Update. Neurology. 2021 Jan 19;96(3):114-122. doi: 10.1212/WNL.0000000000011124. Epub 2020 Nov 3.
- Wiendl H, Abicht A, Chan A, et al; Guideline for the management of myasthenic syndromes. Ther Adv Neurol Disord. 2023 Dec 26;16:17562864231213240. doi: 10.1177/17562864231213240. eCollection 2023.
Sobre el autorVer biografía completa
Actualizado por

Dr Caroline Wiggins, MRCGP
Médico General, Autor Médico
MBBS Honores (con Distinción), MRCGP (2016), MSc.SEM (con Distinción), BSc (Hons)
La Dra. Caroline Wiggins es una médica de cabecera suplente actualmente en el suroeste de Inglaterra.
Acerca del revisorVer biografía completa

Dra. Rachel Hudson, MRCGP
Médico General y Autor Médico
MBChB, MRCGP (2008), BSc (Medical Science), DFSRH, DRCOG, DCH
La Dra. Rachel Hudson es una médica de cabecera del NHS que trabaja en el noroeste de Inglaterra.
Historial del artículo
Artículo también disponible en Inglés, Alemán, Español, Francés, Italiano, Portugués, Hindi, Hebreo, Árabe, y Sueco.
Próxima revisión prevista: 20 de mayo de 2028
21 de mayo de 2025 | Última versión
Únete a la conversación
Comparte tus pensamientos o experiencias con otros en nuestro comunidades de pacientes.

Pregunta, comparte, conecta.
Navega por discusiones, haz preguntas y comparte experiencias en cientos de temas de salud.

¿Te sientes mal?
Evalúa tus síntomas en línea de forma gratuita
Suscríbete al boletín de Patient
Tu dosis semanal de consejos de salud claros y confiables, escritos para ayudarte a sentirte informado, seguro y en control.
Al suscribirte aceptas nuestros Política de Privacidad. Puedes darte de baja en cualquier momento. Nunca vendemos tus datos.