Hernias inguinales
Revisado por Dr Toni Hazell, FRCGPÚltima actualización por Dr Philippa Vincent, MRCGPÚltima actualización 1 Oct 2026
Cumple con las directrices editoriales
- DescargarDescargar
- Compartir
- Language
- Discusión
- Versión en audio
- Agregar a fuentes preferidas en Google
Profesionales Médicos
Los artículos de Referencia Profesional están diseñados para ser utilizados por profesionales de la salud. Están escritos por médicos del Reino Unido y se basan en evidencia de investigación, así como en guías del Reino Unido y Europa. Puede encontrar el Hernia artículo más útil, o uno de nuestros otros artículos de salud.
What is an inguinal hernia?
An abdominal hernia comprises a protrusion of abdominal contents through the fascia of the abdominal wall; an inguinal hernia is where this protrudes through the internal inguinal ring. Hernias contain a portion of peritoneal sac and may contain viscera, usually small bowel and omentum.
Hernia inguinal
Inguinal hernia epidemiology
Inguinal hernias are common, making up 75% of all abdominal hernias.
Inguinal hernias are more common in men (the lifetime risk of an inguinal hernia is 27-43% in men and 3-6% in women).1 Although they are much more common in men, women with a groin hernia are still more likely to have an inguinal than a femoral hernia.2
As well as male sex, risk factors include increasing age (although there is also a significant spike in cases below the age of 5 years) and a genetic predisposition.2
Other risk factors are thought to include: smoking, chronic obstructive pulmonary disease, lower body mass index, high intrabdominal pressure, thoracic or abdominal aortic aneurysm, patent processes vaginalis, history of open appendectomy, peritoneal dialysis, and collagen vascular disease.2
Inguinal hernia presentation
An inguinal hernia will usually present as a swelling in the groin that may appear with lifting and be accompanied by sudden pain.
There may be a cough impulse. The hernia may not be visible when lying flat but may appear on standing.
The hernia may be reducible.
Indirect hernias can cause pain in the scrotum and cause a 'dragging sensation'.
Congenital inguinal hernias are usually detected at birth and all need urgent outpatient referral for surgical repair.
Inguinal hernias in older children and adults usually develop gradually but can occur suddenly with an episode of heavy lifting:
At first appearance, a hernia is usually easily reducible when the patient reclines. However, it may require manual replacement if large.
With time, the hernia enlarges and becomes harder to replace, due to fibrous adhesions forming.
When it can no longer be reduced, it is irreducible or incarcerated. This can occur at any time, as can strangulation. This occurs when visceral contents of the hernia become twisted or entrapped by the narrow opening. This compromises the blood supply, causing swelling and eventually infarction. Strangulation usually leads to bowel obstruction.
There are two types of inguinal hernia:
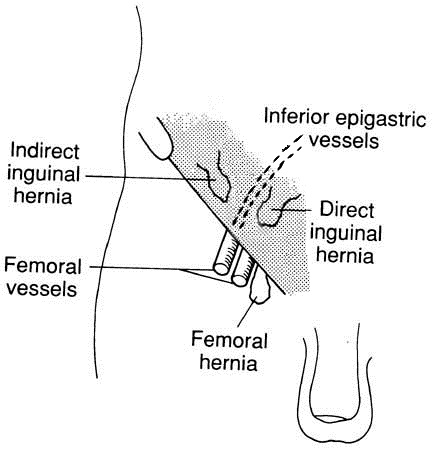
Indirect: a protrusion through the internal inguinal ring passes along the inguinal canal through the abdominal wall, running laterally to the inferior epigastric vessels. This is the more common form accounting for 80% of inguinal hernias, especially in children. It is associated with failure of the inguinal canal to close properly after passage of the testis in utero or during the neonatal period.
Directo: the hernia protrudes directly through a weakness in the posterior wall of the inguinal canal, running medially to the inferior epigastric vessels. It is more common in the elderly and rare in children.
Evaluación3
Examine the patient both standing and lying and ask them to cough or strain.
Insert a finger through the top of the scrotum into the external inguinal ring and palpate for a lump when coughing - cough impulse.
Sliding hernias are probable with large scrotal hernias.
Diagnóstico diferencial
Vea también el separado Bultos en la ingle y el escroto artículo.
Hidrocele (when differentiating from an inguinoscrotal hernia, note that it is possible to get above a hydrocele on examination).
Spermatic cord hydrocele.
Lymph node swelling.
Abscess.
Saphena varix.
Sangrado.
Investigaciones
Whilst most specialists agree that imaging is not necessary to make the diagnosis, in the UK there are often local constraints on referrals for hernia repair which mean that the diagnosis needs to be confirmed by imaging. Ultrasound scan is the imaging option of choice.34
Inguinal hernia treatment and management
Adultos5 2
If the inguinal hernia is small, the patient may only need reassurance. There is good recent evidence that "watchful waiting" is a safe option for many adults with inguinal hernias. Long-term follow-up of these patients suggests that around 68% proceed to surgical management eventually, usually due to worsening pain or lifestyle limitations from progression.2
Patients with pain, reduced mobility or other symptoms should be offered surgical management. Many patients with chronically incarcerated hernias may be asymptomatic but patients with obstruction or strangulation are a surgical emergency.
However, there is always the chance of it becoming a surgical emergency through obstruction and incarceration. Episodes of pain and tenderness suggest the need for urgent treatment but when these become prolonged and severe then emergency surgery is indicated for possible strangulation. The fundamentals of indirect inguinal hernia treatment are the same regardless of the patient's age. Reduction or excision of the sac and closure of the defect with minimal tension are the essential steps in any hernia repair.
Surgical guidelines recommend tailoring the choice of surgery to individual patient factors. Surgical options include either an open (tissue- or mesh-based) procedure or a minimally invasive (laparoscopic or robotic) procedure.
An open repair with mesh is associated with a 50%-75% lower risk of hernia recurrence, lower risk of chronic pain post-operatively, and an earlier return to work compared with a sutured repair. A tissue (sutured) repair is usually used where mesh is contraindicated, for example where there may be potential for infection from a contaminated field. Laparoscopic repair is recommended for bilateral inguinal hernias as the same port sites can be used.
Studies have shown no significant difference between mesh, laparoscopic and robotic procedures in terms of post-operative haematoma, surgical site infection, urinary retention, or hospital length of stay. However post-operative chronic pain appears to be lower in patients who have undergone laparoscopic procedures, though studies have been of questionable quality.
Inguinal hernias in children
The incidence of incarcerated or strangulated hernias in paediatric patients is higher than in adults, at around 7-11%.6 It is higher in infants than in older children. The risk increases with waiting time from diagnosis to procedure.67
Surgical repair is usually recommended as early as possible in paediatric patients because of these risks.
Laparoscopic repair has been shown to have better outcomes than open repair though both have low risks of complications.8910
Complicaciones
Estas incluyen:
Post-operative chronic pain is reported to occur in between 8 and 16% of patients, though laparoscopic repair appears to reduce the risk.2
Recurrence: 1.0% - most happening within five years of operation. Recurrence rate increases:
In children aged younger than 1 year.
In elderly patients.
After incarcerations.
In those with ongoing increased intra-abdominal pressure.
Where there is growth failure.
With prematurity.
Where there are chronic respiratory problems.
In girls with sliding hernias.
Infarcted testis or ovary with atrophy.
Infección de la herida.
Bladder injury.
Intestinal injury.
A hydrocele from fluid accumulation in the distal sac usually resolves spontaneously but sometimes requires aspiration.
Pronóstico
This is generally very good, depending on comorbidity.
Actualizaciones exclusivas para profesionales de la salud
Mantente informado con las últimas actualizaciones clínicas, perspectivas profesionales y orientación basada en evidencia. El boletín de Patient Pro selecciona contenido esencial para profesionales de la salud, entregado directamente en tu bandeja de entrada.
Al suscribirte aceptas nuestros Política de Privacidad. Puedes darte de baja en cualquier momento. Nunca vendemos tus datos.
Lecturas adicionales y referencias
- Jorgenson E, Makki N, Shen L, et al; A genome-wide association study identifies four novel susceptibility loci underlying inguinal hernia. Nat Commun. 2015 Dec 21;6:10130. doi: 10.1038/ncomms10130.
- Gudigopuram SVR, Raguthu CC, Gajjela H, et al; Inguinal Hernia Mesh Repair: The Factors to Consider When Deciding Between Open Versus Laparoscopic Repair. Cureus. 2021 Nov 16;13(11):e19628. doi: 10.7759/cureus.19628. eCollection 2021 Nov.
- Tigora A, Radu PA, Garofil DN, et al; Modern Perspectives on Inguinal Hernia Repair: A Narrative Review on Surgical Techniques, Mesh Selection and Fixation Strategies. J Clin Med. 2025 Jul 9;14(14):4875. doi: 10.3390/jcm14144875.
- Current status of inguinal hernia management; P J McBee et al; International Journal of Abdominal Wall and Hernia Surgery
- Hassler KR, Saxena P, Baltazar-Ford KS; Open Inguinal Hernia Repair.
- LeBlanc KE, LeBlanc LL, LeBlanc KA; Inguinal hernias: diagnosis and management. Am Fam Physician. 2013 Jun 15;87(12):844-8.
- HerniaSurge Group; International guidelines for groin hernia management. Hernia. 2018;22(1):1-165. doi:10.1007/s10029-017-1668-x
- Olesen CS, Mortensen LQ, Oberg S, et al; Risk of incarceration in children with inguinal hernia: a systematic review. Hernia. 2019 Apr;23(2):245-254. doi: 10.1007/s10029-019-01877-0. Epub 2019 Jan 12.
- Retrospective Cohort Study on Inguinal Hernia in Children: Infant Vulnerability to Incarceration and Pediatricians’ Awareness; A G Grewal et al; CHRISMED Journal of Health and Research
- Ma Q, Liu X, Zou Z, et al; Surgical methods and outcomes of inguinal hernia repair in children, adolescents and young adults in a retrospective cohort study. Sci Rep. 2025 Mar 17;15(1):9220. doi: 10.1038/s41598-025-93841-5.
- Morgado M, Holland AJ; Inguinal hernias in children: Update on management guidelines. J Paediatr Child Health. 2024 Nov;60(11):648-653. doi: 10.1111/jpc.16677. Epub 2024 Sep 25.
- A 10-year review of pediatric inguinal hernia management at a tertiary center; B Yu et al; Frontiers in Pediatrics
Sobre el autorVer biografía completa
Actualizado por

Dra. Philippa Vincent, MRCGP
Médico General, Autor Médico
MB BS, Bsc, MRCGP (2000), DCH, DFSRH, DRCOG
Dra Philippa Vincent es un médico de cabecera del NHS que trabaja en el norte de Londres.
Acerca del revisorVer biografía completa

Dr Toni Hazell, FRCGP
MBBS, BSc, FRCGP, DFSRH, Dip GU med, DRCOG, DCH (London, UK, 2000)
La Dra. Toni Hazell se graduó de la Escuela de Medicina del Hospital St. Mary y realizó su VTS en el Hospital Northwick Park.

Pregunta, comparte, conecta.
Navega por discusiones, haz preguntas y comparte experiencias en cientos de temas de salud.

¿Te sientes mal?
Evalúa tus síntomas en línea de forma gratuita
Más en historia y examen
- Pérdida de peso anormal
- Trastorno por consumo de alcohol: reconocimiento y evaluación
- Certificación de defunción
- Enfermedades dentales y periodontales
- Examen de los nervios craneales
- Exoftalmos
- Historia y examen genitourinario - masculino
- Niño enfermo y febril
- Dolor en la fosa ilíaca izquierda
- Síntomas del tracto urinario inferior en mujeres
- Síndrome de Marfan
- Deterioro cognitivo leve
- Dolor de cuello (cervicalgia) y tortícolis
- Trastorno de pesadillas
- Hinchazones orbitales
- Enfermedad arterial periférica
- Historia reumatológica, examen e investigaciones
- Dolor en la fosa ilíaca derecha
- Escalofríos
- Revisión del bebé a las seis semanas