Eritema multiforme
Revisado por Dr Doug McKechnie, MRCGPÚltima actualización por Dr Philippa Vincent, MRCGPÚltima actualización 14 Mar 2025
Cumple con las directrices editoriales
- DescargarDescargar
- Compartir
- Language
- Discusión
- Versión en audio
- Agregar a fuentes preferidas en Google
Profesionales Médicos
Los artículos de Referencia Profesional están diseñados para ser utilizados por profesionales de la salud. Están escritos por médicos del Reino Unido y se basan en evidencia de investigación, así como en guías del Reino Unido y Europa. Puede encontrar uno de nuestros artículos de salud más útil.
What is erythema multiforme?
Erythema multiforme (EM) is a skin condition due to an immune-mediated hypersensitivity reaction to infections or drugs.12 It presents as a dermatological eruption featuring iris or target lesions, although other forms of skin lesion can occur - hence the name. It is usually an acute, self-limiting disease that affects the skin. Mucosal lesions are present in 25% to 60% of patients with erythema multiforme.
EM must be distinguished from the rare but more serious and life-threatening conditions, Stevens-Johnson syndrome (SJS) y necrólisis epidérmica tóxica (NET).3
How common is erythema multiforme? (Epidemiology)2
Erythema multiforme can occur at any age but most commonly presents between the ages of 20 and 40. 20% of cases occur in children. Males are affected slightly more often than females with a ratio of 5:1. Erythema multiforme occurs equally in all ethnic groups. The prevalence is thought to be considerably lower than 1%.
Causes of erythema multiforme (aetiology)1 2
90% of cases of erythema multiforme are caused by infections.
Infecciones
Herpes simplex virus (HSV) 1 and 2 infections (account for >50% of cases).
Mycoplasma pneumonia infections.
Fungal infections.
Other viruses (varicella-zoster virus, cytomegalovirus, hepatitis C virus, and HIV).
Reacciones a medicamentos
Barbiturates.
Penicillins.
Fenotiazinas.
Sulfonamides.
Anticonvulsivos.
Antiinflamatorios no esteroideos.
Vaccinations (diphtheria-tetanus, hepatitis B, smallpox, covid-19).
Otras causas
Heavy metals.
Topical therapies.
Remedios herbales.
Poison ivy.
Symptoms of erythema multiforme (presentation)1 2
Historia
There may be either no prodrome or a mild upper respiratory tract infection. The rash starts abruptly, usually within three days. It starts on the extremities, being symmetrical and spreading centrally.
There may be some mild burning or itching sensation but the skin is not tender.
Recurrent EM is thought to be usually due to reactivation of HSV.
Half of children with the rash have recent herpes labialis. It usually precedes the EM by 3 to 14 days but it can sometimes be present at the onset.
Examen
The iris or target lesion is the classical feature of the disease.
Initially, there is a dull red macule or urticarial plaque that enlarges slightly up to 2 cm over 24-48 hours. In the middle, a small papule, vesicle or bulla develops, flattens, and then may clear. The intermediate ring forms and becomes raised, pale and oedematous. The periphery slowly becomes violaceous and forms a typical concentric target lesion.
The lesions can expand to form plaques which are several centimetres in diameter.
Some lesions are atypical targets with only two concentric rings. Polycyclic or arcuate lesions may occur.
Eritema multiforme
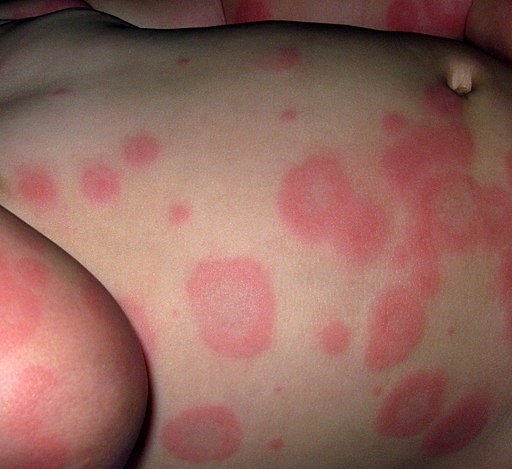
Eritema multiforme
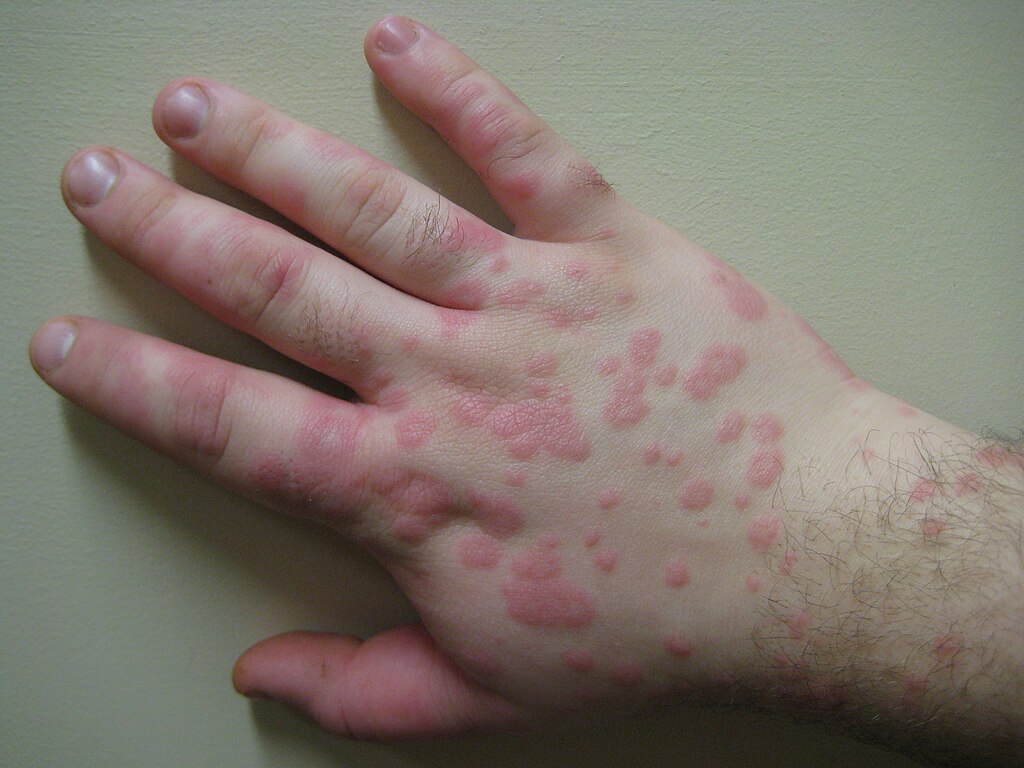
Köbner's phenomenon may occur. This lesion occurs along the line of previous skin trauma.
Lesions appear first on the extensor surfaces of the periphery and extend centrally. The palms, neck and face are often involved but the soles and flexures of the extremities less often.
There may be mucosal involvement. Whereas the skin lesions are painless, mucosal lesions are often painful. Oral lesions are most common with lips, palate and gingiva affected; urogenital and ocular membranes have also been known to have been affected.2
Occasionally the mucosal involvement is marked with few skin lesions.
Diagnosing erythema multiforme (investigations)
Usually, no specific investigations are indicated.
Skin biopsy can be indicated in an atypical presentation or where there is recurrent EM without an obvious trigger.
Investigations may be required to discover the underlying cause - eg, CXR, drug history, atypical pneumonia titres.
An FBC will often show moderate leukocytosis, eosinophilia, neutropenia, mild anaemia, and thrombocytopenia.
ESR may be elevated in severe cases.
CXR may show interstitial disease if the underlying cause is Mycoplasma pneumoniae.
If the diagnosis is unclear, a skin biopsy may be suggested.
Diagnóstico diferencial4
SJS.
TEN.
Penfigoide.
Management of erythema multiforme6
If a drug is thought to be responsible, it must be withdrawn. If an infection is suspected, it should be treated.
In recurrent disease due to HSV, antiviral therapy is beneficial.7
Symptomatic treatment may include analgesics, mouthwash and local skin care. Steroid creams may be used.
It may be helpful to emphasise to patients or parents that, although an underlying infection may be contagious, EM itself is not.
If the mouth is very sore, attention may have to be given to hydration and nutrition.
Dilute antiseptics, such as chlorhexidine, may help to prevent secondary infection. Lubricating drops for the eyes may be required.
Where erythema multiforme is severe and refractory, biologic agents such as thalidomide, anti-TNF, apremilast, rituximab, and JAK inhibitors have been shown to have some benefit.8
Complications of erythema multiforme
Secondary infection of lesions may occur. Serious complications are unusual in an immunocompetent patient. A very sore mouth may lead to dehydration and poor nutrition. Genitourinary lesions may result in urinary retention. If the eye is involved it is important to prevent infection or conjunctival scarring.
Significant mucosal involvement indicates erythema multiforme major which is likely to required hospitalisation for supportive care.9
Pronóstico1
Skin lesions usually heal without complication, but skin hyperpigmentation may occur. Some episodes of erythema multiforme have been documented to persist for up to five weeks, and recurrent and more persistent forms may occur. Mucosal lesions can lead to adhesions; in the case of ocular involvement this can result in blindness. 2
Actualizaciones exclusivas para profesionales de la salud
Mantente informado con las últimas actualizaciones clínicas, perspectivas profesionales y orientación basada en evidencia. El boletín de Patient Pro selecciona contenido esencial para profesionales de la salud, entregado directamente en tu bandeja de entrada.
Al suscribirte aceptas nuestros Política de Privacidad. Puedes darte de baja en cualquier momento. Nunca vendemos tus datos.
Lecturas adicionales y referencias
- Hafsi W, Badri T; Erythema Multiforme. StatPearls, 2021.
- Trayes KP, Love G, Studdiford JS; Erythema Multiforme: Recognition and Management. Am Fam Physician. 2019 Jul 15;100(2):82-88.
- Hafsi W, Badri T; Erythema Multiforme.
- Harr T, French LE; Toxic epidermal necrolysis and Stevens-Johnson syndrome. Orphanet J Rare Dis. 2010 Dec 16;5:39.
- Trayes KP, Savage K, Studdiford JS; Annular Lesions: Diagnosis and Treatment. Am Fam Physician. 2018 Sep 1;98(5):283-291.
- Alergia a medicamentos: diagnóstico y manejo de la alergia a medicamentos en adultos, niños y jóvenes; Guía clínica de NICE (septiembre 2014; actualizada noviembre 2018).
- Soares A, Sokumbi O; Recent Updates in the Treatment of Erythema Multiforme. Medicina (Kaunas). 2021 Sep 1;57(9):921. doi: 10.3390/medicina57090921.
- Sladden MJ, Johnston GA; Infecciones cutáneas más comunes en niños. BMJ. 21 de mayo de 2005;330(7501):1194-8.
- Eritema multiforme; E Kechichian et al, Science Direct
- Erythema Multiforme; DermNet
Sobre el autorVer biografía completa
Actualizado por

Dra. Philippa Vincent, MRCGP
Médico General, Autor Médico
MB BS, Bsc, MRCGP (2000), DCH, DFSRH, DRCOG
Dra Philippa Vincent es un médico de cabecera del NHS que trabaja en el norte de Londres.
Acerca del revisorVer biografía completa

Dr Doug McKechnie, MRCGP
Redactor Médico
MA, MBBS, MSc, DRCOG, MRCP(UK), MRCGP(2021), FHEA
El Dr. Doug McKechnie es un médico de cabecera del NHS que trabaja en Londres. Trabaja a tiempo completo en la práctica clínica y también es el Subdirector del módulo de Práctica Clínica y Profesional en la Escuela de Medicina del University College London.

Pregunta, comparte, conecta.
Navega por discusiones, haz preguntas y comparte experiencias en cientos de temas de salud.

¿Te sientes mal?
Evalúa tus síntomas en línea de forma gratuita
Más en dermatología
- Acné vulgar
- Fenómenos alérgicos
- Alopecia
- Lesión por frío
- Historia y examen dermatológico
- Dermatofitosis
- Pie diabético
- Eritema indurado
- Eritema nodoso
- Eritrodermia
- Hemangiomas de la piel
- Nevus de halo
- Trombocitopenia inmune
- Síndrome de Klippel-Trénaunay
- Erupción polimórfica lumínica
- Mancha de vino de Oporto
- Artritis psoriásica
- Escarlatina
- Dermatitis seborreica
- Nódulos cutáneos y subcutáneos